Sources checked: . Sources and review scope.
Stress-test code selection depends on the service performed, the components furnished, and the billing arrangement. These examples are a starting point, not a claim recipe. Check current CPT instructions, Medicare component indicators and edits, and the patient's coverage rules for the date of service.
3% of collectionsNo setup feeNo contract

93015 describes the complete stress-test service, including supervision, ECG tracing, interpretation, and report. Codes 93016, 93017, and 93018 describe component services. Report only the work furnished and supported by the record. Who may bill each component depends on the service arrangement, current Medicare payment indicators, and payer rules, not equipment ownership alone.
The CPT component descriptors identify 93016 as supervision, 93017 as tracing, and 93018 as interpretation and report. Confirm the current codebook instructions and report only work furnished and supported by the record.
For hospital services, physician and facility claims may report different components. Confirm who furnished each component, whether separate reporting is allowed, and the facility's billing arrangement before assigning 93016, 93017, or 93018.
When providers split a test, identify who furnished each component and check current CPT rules and Medicare professional/technical component indicators before billing. Do not assign a component to a practice just because it owns the equipment.
The stress-test tracing is described within the stress-test service. Report a separate ECG only when documentation and current CPT and NCCI rules support it.
Cardiac stress test billingMedicare's required supervision level depends on the specific test and applicable rules. Check 42 CFR § 410.32 and current payment policy for the service and date. Document the practitioner who actually furnished or supervised the test, and report it under applicable qualification, enrollment, and billing rules.
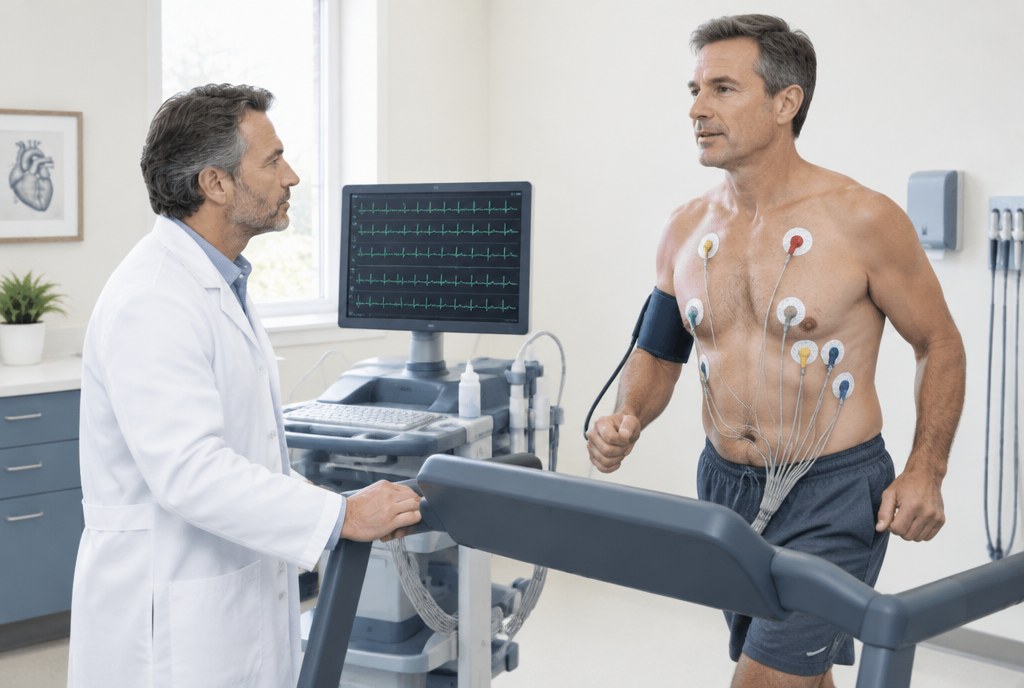
An NP or PA may furnish diagnostic services only when applicable Medicare requirements, state scope of practice, and enrollment rules permit it. Verify those conditions for the specific test before billing a component under that practitioner's NPI.
Do not report a practitioner as supervising when the record does not support that role. For drug stress, document who furnished or supervised the service and apply the standard for that test.
A stress echo is reported under the code and components that match the work performed. Check the current CPT descriptor and instructions for 93350 and 93351; do not infer a code solely from the office or hospital setting.
Modifier 26 is appropriate only when the current Medicare Physician Fee Schedule component indicator and billing facts support professional-component reporting. Apply current CPT and NCCI rules to separately billed stress-test components; supervision or reading alone does not establish that a particular code combination is reportable.
Before reporting separate stress-test or contrast lines with a stress echo, check current CPT instructions and the NCCI edit file for the exact code pair and circumstances. Use 93352 only when the documented service meets current add-on instructions.
For a nuclear study, imaging, stress-test, radiopharmaceutical, and drug lines depend on which services were furnished and who may bill them. Check current CPT and HCPCS descriptors, component indicators, and facility or payer rules before combining these services on a claim.
78452 CPT codeCheck CPT
Match code to work furnished
Check NCCI
Identify each service furnished
Use the stress-test code that describes the documented service, whether exercise or pharmacologic stress was used. Verify current CPT instructions for the service performed.
For a separately reported drug, confirm the current HCPCS Level II descriptor, billing unit, actual dose, and applicable payer rules. A purchase alone does not establish that a drug line is separately payable.
Do not assume an IV start, injection, or other service is separately reportable or included without checking current code descriptors, CPT instructions, and NCCI edits.
Before submitting a stress-test claim, check:
These are code families, not universal claim combinations. Check current CPT instructions, Medicare component indicators and NCCI edits, rendering arrangement, and payer rules for the service date.
Cardiac stress test billing| Setting | Treadmill | Stress echo | Nuclear |
|---|---|---|---|
| Office | Select code(s) for documented components | Check CPT descriptor and component rules | Check imaging, stress, drug, and tracer rules |
| Hospital physician claim | Report professional work only when indicator permits | Check CPT and component indicators | Check component indicator and NCCI edits |
| Hospital facility claim | Report components furnished under facility rules | Follow current facility coding rules | Check facility rules for imaging and supplied agents |
93015 describes a complete stress-test service; 93016, 93017, and 93018 describe components. Which entity reports a component depends on the service arrangement and applicable coding and payment rules.
Regadenoson is the stress agent, not a single CPT code. Imaging, stress-test, drug, and tracer codes depend on the study performed, current CPT/HCPCS descriptors, and payer rules. Verify each line and unit before billing.
Only when Medicare requirements, state scope, and enrollment rules permit that NP to furnish or supervise the specific test. Confirm the applicable rule before billing under the NP's NPI.
93017 describes the tracing component. 93015 describes the complete service. Confirm the current CPT descriptors and applicable component rules for the service billed.
Reviewed on 2026-09-30 against official source pages for Medicare NCCI procedure-to-procedure edits and policy, the Medicare Physician Fee Schedule, diagnostic-test conditions, Medicare coverage documents, and AMA CPT resources:
This source check reviewed coding-resource and coverage references, not every CPT instruction, code pair, fee-schedule indicator, claim scenario, state scope rule, or payer contract. It is not a clinical review, legal advice, or a guarantee of coverage or reimbursement. Verify the applicable current sources and plan requirements before submitting a claim.
We show you, by payer, which went out with the wrong setting or supervising name. Free, no strings.
3% of collectionsNo setup feeNo contract